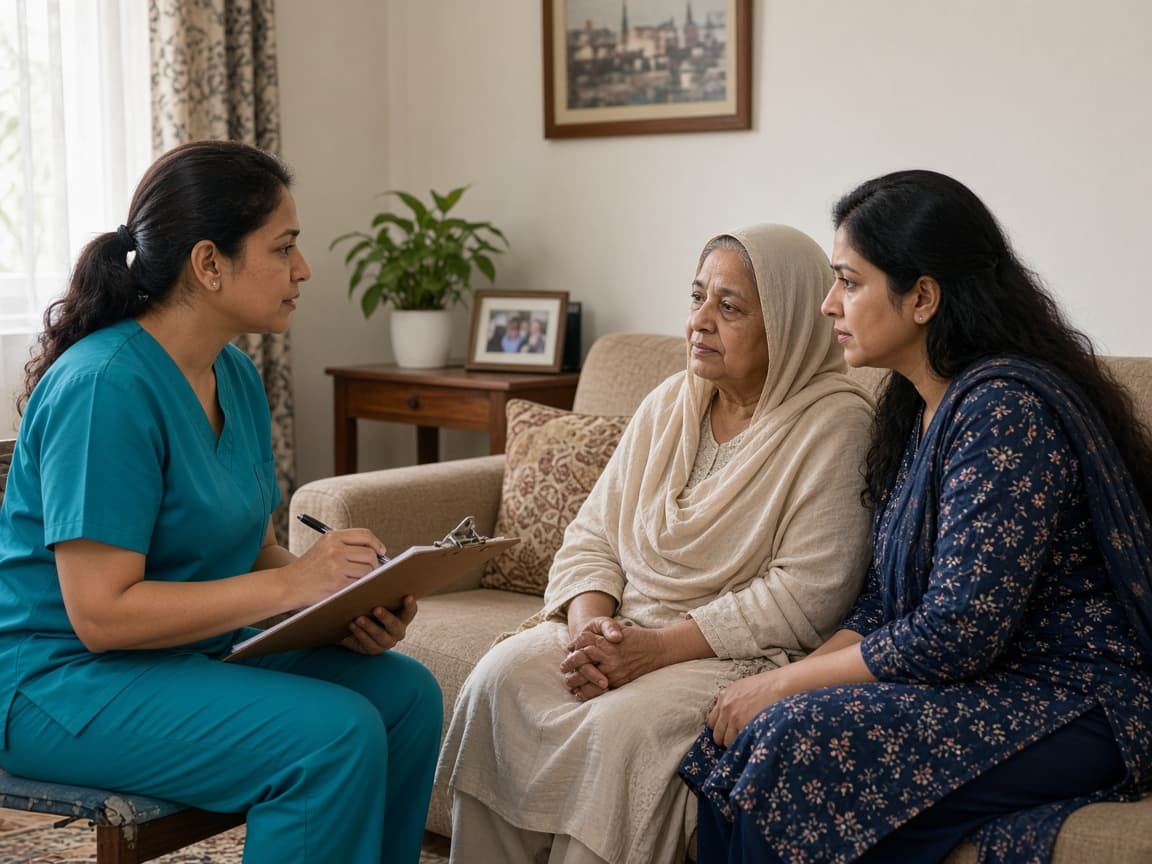A home physiotherapy visit is a clinical appointment in the place the person actually lives. The World Health Organization describes rehabilitation as care that helps people take part in everyday activities when a health condition has made those activities difficult. NHS physiotherapy works in the same direction: assessment, movement, advice, and a plan that continues between appointments.
The visit has a narrow job. The therapist looks at how the person moves today, practises a few movements that match that finding, teaches the relative who will be there in the morning, and leaves the plan in writing. A household that knows those four parts can use the hour well.
What the therapist is looking at
The therapist will usually ask what changed after hospital or after the injury, which movement hurts, and which task the family most wants back. Standing to reach the toilet, getting off the chair, or managing the indoor stairs are common answers. The answer shapes the session more than a general exercise list does.
They watch the person move from lying to sitting, and from sitting to standing, if those transfers are allowed. If walking is permitted, they watch a short path inside the house, including the turn at the doorway. They notice breathlessness, dizziness on standing, and how much of the effort is coming from the helper.
They also watch the helper's hands. Pulling on an arm, standing too far away, or asking someone to rise from a low plastic chair without arms are methods they will often change on the spot. The chair in the room matters. Describe it at the start if it is soft, low, or unstable.
Basic exercises for elderly mobility names a few movements families sometimes discuss for an older adult. Treat that page as a vocabulary for the appointment. The therapist decides whether any of those movements belong in this house, this week.
The paper they should leave behind
A usable plan names each movement and the position: lying, sitting, or standing. It records how many repetitions the therapist chose, or whether they asked only for the movement to be practised during a real task such as standing up for a meal. Those numbers come from the therapist. A general article cannot supply them.
The plan should also say what "stop" means for this person. Sharp or rising pain, dizziness, chest pain, and breathlessness that interrupts a sentence are usual reasons to end the session and contact the team. Mild familiar ache that settles after rest is a different report, and the therapist should say which one they expect.
Surgical limits stay on the same page. How much weight the leg may take, whether a brace stays on, and any bending restriction were set by the surgeon. The home visit works inside that instruction. Following a home exercise program is about reading the paper afterwards without adding drills from a video.
Three things the visit cannot replace
Emergency care comes first. Collapse, severe breathlessness, chest pain, heavy bleeding, or a sudden change in consciousness need urgent medical help, even if a therapist is due that afternoon.
A written restriction still holds when everyone feels hopeful. Families sometimes allow a fuller step, a deeper bend, or time without the brace because one attempt looked easy. That change is the surgeon's decision, made with the notes in front of them.
A day when the person is too unwell is a day to wait. Fever, repeated vomiting, a wound that has opened, or a new hot swollen calf are reasons to speak to the clinic before anyone starts the list. Skipping practice on that day is part of safe rehabilitation, which often runs unevenly over weeks. Rehabilitation after injury describes that longer stretch.
Questions worth the last ten minutes
Write the answers on the plan, in the language the morning helper reads.
- Which movements are for this person this week, and which should we leave out even if a relative found them online?
- Where should the helper's hands be during standing, and which arm must not be pulled?
- Are the stairs allowed yet, or is walking to the toilet on this floor the only goal?
- Who answers the phone if swelling or pain changes tonight, and which hospital holds the record?
- What should we write down before the next review?
Ask the therapist to watch the family member complete one repetition of each movement. Hand placement and the height of the chair show up in that minute, and they are harder to correct from a later phone call.
Between one visit and the next
Keep the plan where it will be seen, not in a bag of discharge papers. A few lines after each session, recording what was possible and whether dizziness or pain appeared, give the next appointment something solid to adjust.
If the person's condition changes, pause the movements and contact the team that set the limits. Home physiotherapy supports that medical plan. The plan remains the authority when the house feels quiet and a relative is tempted to push ahead.
"Near me" is an address problem. A therapist who covers a whole city still needs the ward, the floor, and the stair. Home care in Kathmandu, Pokhara, and Lalitpur, including Sanepa name the limits to give them before the visit. The movements on this page do not change. The ride and the doorway do.